
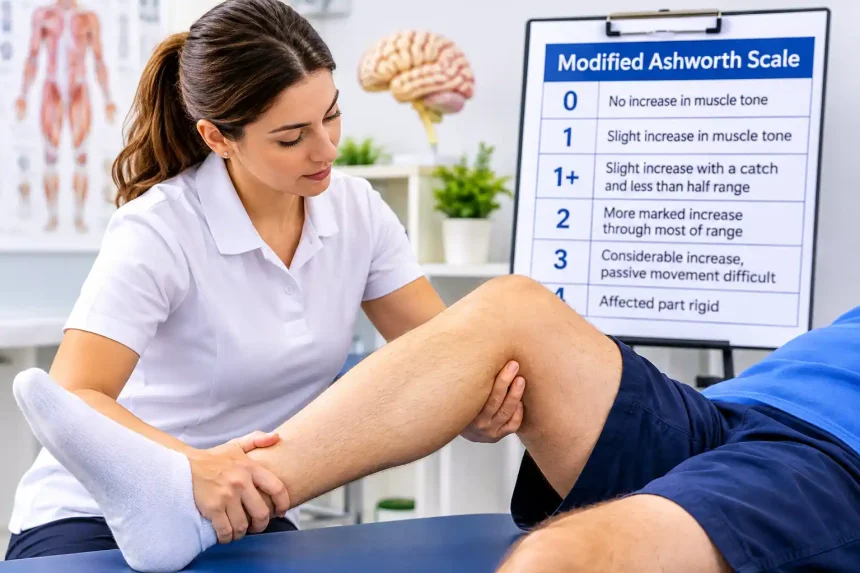
The modified ashworth scale (MAS) is one of the most widely used clinical tools for assessing muscle spasticity, a common and often disabling consequence of neurological injury or disease. First developed as a refinement of the original Ashworth Scale, the MAS converts a clinician’s impression of muscle resistance into a standardised, reproducible grade. For physiotherapists, occupational therapists, neurologists and rehabilitation physicians across the United Kingdom and the United States, it remains a familiar and practical bedside measure. Understanding how to perform it correctly, how to interpret its grades, and where its limitations lie is essential for anyone involved in neurological rehabilitation.
This article explains what the Modified Ashworth Scale is, how it works, and how healthcare professionals use it in everyday clinical practice.
What Is the Modified Ashworth Scale?
The Modified Ashworth Scale is a clinical rating scale used to grade the resistance a clinician feels when passively moving a joint through its range of motion. That resistance, when it is velocity-dependent and arises from an exaggerated stretch reflex, reflects spasticity — a hallmark of upper motor neurone (UMN) syndrome. The scale was introduced in 1987 by Richard Bohannon and Melissa Smith, who added an intermediate grade (1+) to the original Ashworth Scale to capture the many patients whose tone sat between “slight” and “more marked” increases.
The MAS assigns an ordinal score, typically from 0 to 4, where lower scores represent normal or near-normal muscle tone and higher scores indicate progressively greater stiffness or resistance. Because it is quick, requires no equipment, and can be performed at the bedside or in an outpatient clinic, the MAS has become an international standard for muscle spasticity assessment in routine care and in clinical research.
What the Scale Actually Measures
To use the scale correctly, it helps to understand precisely what it is — and is not — measuring. The MAS measures the resistance to passive movement at a single joint, performed at a reasonably fast pace. This resistance has two possible sources:
- Neural (reflex-mediated) resistance: caused by an exaggerated stretch reflex, this is the defining feature of true spasticity. It often emerges as a sudden “catch” followed by a release (the “clasp-knife” phenomenon).
- Non-neural (mechanical) resistance: caused by changes in the muscle tissue itself, including stiffness, fibrosis or shortening after prolonged immobilisation.
The MAS cannot perfectly separate these two components, which is an important caveat when interpreting results. A high score may reflect genuine spasticity, soft-tissue changes, or a combination of both.
Crucially, the scale is not a direct measure of function. It tells the clinician about muscle tone in a relaxed, passive limb, but it does not predict how well a person can walk, grip or dress. For this reason, the MAS should be used alongside functional measures and never as a standalone diagnostic or decision-making tool.
Modified Ashworth Scale Grades: The Six Scoring Categories
The Modified Ashworth Scale grades form a six-point ordinal scale. Although often described as a “5-point plus” scale, in clinical practice most teams refer to six distinct categories: 0, 1, 1+, 2, 3 and 4.
Grade 0
No increase in muscle tone. The limb moves through its full, available range with no abnormal resistance. This is the expected finding in a healthy limb or a fully recovered one.
Grade 1
Slight increase in muscle tone. The examiner feels a minimal resistance at the end of the range of motion (a “catch and release”) or very brief, minimal resistance throughout the movement when the limb is moved into flexion or extension. Movement is otherwise full and smooth.
Grade 1+ (the distinguishing grade)
Slight increase in muscle tone with a catch, followed by minimal resistance throughout the remainder (less than half) of the range of motion. This is the grade that Bohannon and Smith added to improve the discrimination of the original scale. It captures mild but clearly detectable spasticity that Grade 1 alone failed to describe.
Grade 2
More marked increase in muscle tone through most of the range of motion, but the affected part is still easily moved. The resistance is noticeable across the majority of the movement arc, yet the examiner can move the joint without difficulty.
Grade 3
Considerable increase in muscle tone; passive movement is difficult. The resistance is substantial throughout the range, making it hard for the clinician to move the limb, though full movement can usually still be achieved with effort.
Grade 4
Affected part(s) rigid in flexion or extension. The joint is fixed or nearly fixed, and passive movement is either impossible or achievable only with extreme difficulty. At this level, distinguishing spasticity from an established contracture becomes especially important (see below).
How the Modified Ashworth Scale Assessment Is Performed
Performing the MAS consistently is key to reliable Modified Ashworth Scale interpretation. The procedure generally follows these steps:
- Position the patient. The person should ideally be lying comfortably supine, relaxed and supported, with the limb to be tested positioned to allow full movement at the target joint. Anxiety, pain or a full bladder can raise tone and skew the result, so comfort matters.
- Explain the procedure. Tell the person what you are about to do and ask them to remain as relaxed as possible. Voluntary contraction will mask true passive resistance.
- Passively move the joint once. Move the limb through its full available range to familiarise yourself with the endpoint and to detect any fixed limitation (contracture).
- Perform the graded movement. Move the joint passively through its full range at a speed of approximately one second for the full range, as recommended in standardised protocols. The speed matters because spasticity is velocity-dependent; moving too slowly or too quickly will change the resistance felt.
- Feel for the “catch.” Note the point in the range where a sudden catch or increased resistance occurs, and whether resistance persists beyond it.
- Grade the response according to the six categories above.
- Test both sides and record. Compare the affected limb with the unaffected side, and note the muscle group (for example, “elbow flexors”) rather than a vague “upper limb” label. Document the grade, the joint, the muscle group, and any positioning considerations.
Most protocols recommend testing the limb in the direction opposite to the muscle being assessed — for example, extending the elbow to test elbow flexor tone, or dorsiflexing the ankle to assess plantar flexor spasticity.
Clinical Applications in Neurological Rehabilitation
The MAS is used across a broad range of neurological conditions where UMN syndrome and spasticity occur.
Stroke
Spasticity develops in a significant proportion of people after stroke, often in the upper limb flexors and lower limb extensors. Clinicians use the MAS to monitor tone over time and to evaluate the effect of interventions such as botulinum toxin injections, oral antispasticity medication, stretching or splinting.
Cerebral Palsy
In children and adults with cerebral palsy, spasticity contributes to abnormal postures and reduced function. The MAS provides a simple, repeatable way to screen muscle groups and inform decisions about therapy, orthotics or tone-reducing treatments.
Multiple Sclerosis
Spasticity is one of the most common symptoms of multiple sclerosis, particularly in the lower limbs. The American Physical Therapy Association lists the MAS as a recognised measure for use in MS, where it helps track fluctuating tone and response to medication such as baclofen or tizanidine.
Spinal Cord Injury
After spinal cord injury, spasticity can cause pain, interfere with transfers and limit mobility. Although research has raised concerns about the scale’s reliability in the lower limb in this population, it remains widely used in spinal cord injury rehabilitation settings.
Ashworth Scale Versus Modified Ashworth Scale
Understanding the Ashworth Scale versus Modified Ashworth Scale distinction is useful for clinicians and students alike.
The original Ashworth Scale, published in 1964, was a five-point scale (0–4) that described increasing resistance to passive movement but had relatively broad categories. Its key limitation was a large gap between “slight increase in tone” (Grade 1) and “more marked increase” (Grade 2), into which many patients fell.
The Modified Ashworth Scale, introduced in 1987, added the intermediate Grade 1+ to fill this gap, improving the scale’s sensitivity to mild spasticity. This made the MAS better able to describe the subtle differences frequently seen in clinical practice, particularly in people with mild to moderate spasticity. In most modern settings, the MAS has largely replaced the original because of this added discrimination.
Advantages and Limitations of the Modified Ashworth Scale
Advantages
- Quick and equipment-free: the MAS can be performed in under a minute per joint with no specialised tools.
- Widely recognised: its universal use means scores are easily communicated between clinicians and across services in both the UK and the US.
- Clinically practical: it gives a fast, standardised snapshot of tone that can guide treatment decisions and monitor change over time.
Limitations
- Moderate inter-rater reliability: several studies report only moderate agreement between different clinicians, particularly at the lower end of the scale and in the lower limb after spinal cord injury.
- Cannot separate neural from mechanical resistance: the scale measures the combined effect of spasticity and soft-tissue stiffness, so it may overestimate spasticity in a stiff, contracted muscle.
- Ordinal, not linear: a move from Grade 2 to Grade 3 is not mathematically equivalent to a move from Grade 1 to Grade 2. Scores should be treated as categories, not precise quantities.
- Velocity-dependent variability: unless the movement speed is standardised (about one second through range), results can vary between assessments.
Reliability and Validity
The psychometric properties of the MAS have been examined extensively, with mixed conclusions. Intrarater reliability (the same clinician repeating the test) tends to be better than interrater reliability (agreement between different clinicians). One recent review of the scale after stroke reported good to excellent intrarater reliability for upper limb muscles and moderate to excellent reliability for the lower limb.
By contrast, interrater reliability has been described as only moderate in several studies, with some authors concluding that the scale is of limited use when scores from different examiners are compared directly. This matters in practice: if two clinicians assess the same patient on the same day and record different grades, treatment decisions based on those scores may be inconsistent.
Validity — whether the scale truly measures spasticity — has also been questioned. Criterion validity trials comparing MAS scores with electromyographic (EMG) measures of muscle activity have produced variable results, and the scale’s inability to isolate neural from non-neural resistance is a recognised threat to its construct validity. In short, the MAS is a useful clinical and research tool, but it is not a perfect or fully objective measure of spasticity.
Interpreting and Documenting Results
Good Modified Ashworth Scale interpretation depends on careful documentation. A clinically meaningful record should include:
- The muscle group tested (for example, “left elbow flexors”), not merely “left arm.”
- The grade assigned (0, 1, 1+, 2, 3 or 4).
- The position of the patient during testing.
- Any factors that may have influenced the result, such as pain, anxiety, recent activity or medication timing.
When documenting change, clinicians typically note the direction of change (for example, “elbow flexor tone reduced from 3 to 2 following treatment”) rather than calculating percentage reductions, which are inappropriate for an ordinal scale.
Practical Clinical Examples
Example 1 — Post-stroke upper limb. A 62-year-old man is assessed six weeks after a left middle cerebral artery stroke. Testing the right elbow flexors, the therapist feels a clear catch early in extension, followed by mild resistance for less than half the remaining range. This is recorded as Grade 1+, indicating mild but detectable spasticity worth monitoring.
Example 2 — Multiple sclerosis. A 45-year-old woman with relapsing–remitting MS reports leg stiffness that makes walking difficult. On assessment, her right knee extensors show marked resistance through most of the range, yet the knee is still easily moved. This is recorded as Grade 2.
Example 3 — Cerebral palsy. A child with spastic diplegia has ankles that are difficult to dorsiflex. The therapist finds considerable resistance with passive movement difficult through the full range, recorded as Grade 3 in the plantar flexors bilaterally, informing a review of botulinum toxin dosing and orthotic management.
Spasticity Versus Muscle Stiffness and Contracture
These three terms are often confused, but they describe different problems:
- Spasticity is a velocity-dependent increase in tonic stretch reflexes resulting from UMN damage. Its hallmark is that resistance to movement changes with the speed at which the limb is moved.
- Muscle stiffness is a non-neural increase in resistance arising from changes in the muscle tissue itself — reduced compliance, fibrosis or increased resting tone. It is present across movement speeds and is not reversed by removing the neural drive.
- Contracture is a fixed shortening of muscle, tendon or joint capsule that limits passive range of motion regardless of any reflex activity. A contracture cannot be overcome by slow movement or relaxation.
This distinction matters because the treatment differs: spasticity may respond to medication or botulinum toxin, whereas stiffness and contracture generally require stretching, positioning, splinting or surgery. Because the MAS measures combined resistance, a high grade in a chronically immobilised limb may reflect contracture as much as spasticity — another reason the scale should be interpreted with caution and never used in isolation.
Frequently Asked Questions
What is the Modified Ashworth Scale?
The Modified Ashworth Scale is a clinical tool used to grade the resistance felt when a clinician passively moves a joint, providing a standardised measure of muscle tone and spasticity. It scores from 0 (no increase in tone) to 4 (rigid in flexion or extension), with an intermediate 1+ grade.
What are the six Modified Ashworth Scale grades?
The six Modified Ashworth Scale grades are 0 (no increase in tone), 1 (slight increase, minimal resistance at end range), 1+ (slight increase with a catch and less than half-range resistance), 2 (more marked increase through most of the range, still easily moved), 3 (considerable increase, passive movement difficult) and 4 (rigid in flexion or extension).
How is the Modified Ashworth Scale performed?
The clinician positions the patient comfortably, moves the target joint passively at roughly one second through its range, feels for a “catch” and subsequent resistance, and assigns a grade. The test is performed in the direction opposite to the muscle being assessed.
What does a score of 1+ mean?
A score of 1+ indicates a slight increase in muscle tone with a catch followed by minimal resistance through less than half the remaining range of motion. It describes mild but clearly detectable spasticity and is the grade added to the original Ashworth Scale to improve discrimination.
What is the difference between the Ashworth Scale and Modified Ashworth Scale?
The original Ashworth Scale is a five-point scale (0–4). The Modified Ashworth Scale adds the intermediate 1+ grade to fill the gap between “slight” and “more marked” increases in tone, improving sensitivity to mild spasticity.
What are the limitations of the scale?
The MAS has moderate inter-rater reliability, so different clinicians may record different grades. It measures combined neural and non-neural resistance and cannot distinguish spasticity from stiffness or contracture.It is an ordinal scale, so grades should not be treated as precise numerical quantities.
Who uses the Modified Ashworth Scale?
Physiotherapists, occupational therapists, neurologists, rehabilitation physicians and other clinicians working in neurological rehabilitation commonly use the MAS to assess spasticity in conditions such as stroke, cerebral palsy, multiple sclerosis and spinal cord injury.

